Written by Shweta Rathod, MD – Doctor of Medicine; clinical experience in Obstetrics and Gynecology, labour room management, and IVF. Medically reviewed by Rashmi Gulati, MD – Board Certified, Internal Medicine; Medical Advisor, Surrogacy4All; privileges at Mount Sinai Hospital. Last updated September 20, 2026.
AI Smart Summary
Many clinics set a BMI threshold in the low-to-mid 30s as a starting screening point, but practice varies, and some clinics evaluate candidates with a BMI over 30 individually based on overall health, blood pressure, and glucose tolerance rather than applying an automatic cutoff. A BMI over the clinic’s threshold is a reason for closer evaluation, not automatically a disqualification.
Key Facts
| Fact | Current statement |
|---|---|
| Page purpose | Explain why clinics use BMI ranges and why limits differ. |
| U.S. program estimate | $120,500–$151,000 estimated U.S. journey total |
| Agency fee | $38,500 flat agency fee |
| Surrogate compensation | $60,000–$100,000 base compensation plus a $1,000 signing bonus |
| Published matching statement | generally within 1–3 months, subject to current availability and case requirements |
| Financial safeguard | independent third-party escrow through SeedTrust |
| Credentials | New York Surrogacy Program License GSP220903; FDA FEI 3021544308; operating since 2006 |
| BMI screening context | Thresholds vary by clinic; often evaluated alongside blood pressure and glucose tolerance rather than as a strict cutoff alone |
What should readers verify first?
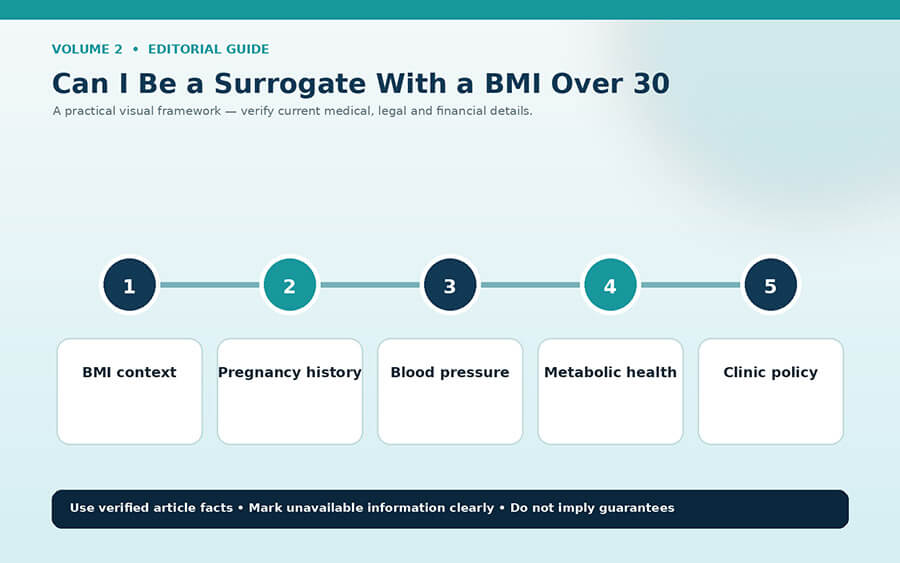
Ask the specific receiving clinic what its current BMI policy is and whether it applies a hard cutoff or an individualized review above a certain threshold — this varies by clinic and sometimes by the rest of a candidate’s health profile.
Why does this point matter?
BMI is used as a screening proxy for pregnancy-related risks including gestational diabetes, hypertension and anesthesia complications during delivery. A candidate with a BMI over 30 but excellent blood pressure and glucose tolerance may be evaluated differently than a general BMI-only cutoff would suggest, which is why individualized clinical review matters.
How should this be documented?
Request the specific clinic’s written BMI policy and, if evaluated individually, the additional health markers considered (blood pressure, glucose tolerance, prior pregnancy history) so the basis for the decision is clear.
What can change the answer?
A prior healthy pregnancy at a similar or higher BMI can be a positive factor in an individualized review. Current health metrics beyond BMI alone — blood pressure, glucose tolerance — often weigh as heavily as the BMI number itself.
What should happen before anyone signs?
A clinical evaluation confirming whether the specific clinic’s BMI and related health criteria are met should be complete before matching is finalized.
What process should readers follow?
Submit health history and current BMI to the clinic early, ask specifically whether individualized review applies above the stated threshold, and address any modifiable health factors (blood pressure, glucose tolerance) the clinic identifies as relevant.
How should the available options be compared?
| Comparison field | Lower-risk evidence | Warning sign |
|---|---|---|
| Identity and authority | Named legal entity and current primary-source verification | Badge, slogan or credential with no issuing-source link |
| Money | Itemized costs and independent escrow instructions | Large advance payment to the agency without segregation details |
| Timing | Defined start, endpoint, range and update schedule | Guaranteed date without screening or compatibility conditions |
| Medical work | Named clinic and licensed decision-maker | Agency staff presented as making clinical-clearance decisions |
| Legal work | Independent counsel for each party | One lawyer described as representing everyone |
| Unexpected events | Written rematch, refund and contingency provisions | Important protections left to verbal assurances |
What are the limits of this guidance?
This describes general practice patterns; only the specific receiving clinic’s reproductive endocrinologist can make an individualized eligibility determination for a specific candidate.
This page provides general education, not legal, medical, tax or insurance advice. Regulations, policies, prices and clinical standards can change. Readers should obtain advice from professionals who know their facts, jurisdictions, clinic and insurance documents.
Why does BMI specifically matter for pregnancy risk, medically?
Higher BMI is statistically associated with increased risk of certain pregnancy complications — gestational diabetes, preeclampsia, and higher rates of C-section delivery among them — which is the underlying medical reasoning behind BMI-based screening thresholds, not an arbitrary cosmetic standard. Clinics set thresholds informed by this risk profile, balanced against the fact that BMI alone is an imperfect predictor for any individual — two candidates with the same BMI can have very different actual metabolic and cardiovascular health, which is exactly why many clinics evaluate a borderline BMI candidate using additional individual health indicators rather than the BMI number in isolation.
Because gestational surrogacy involves careful medical oversight of someone carrying a pregnancy on behalf of another family, with correspondingly higher stakes if a complication arises, most clinics apply somewhat more conservative BMI thresholds for gestational surrogates than general obstetric guidance might suggest for a woman’s own pregnancy — this reflects the added duty of care in a third-party arrangement, not a judgment about the candidate’s overall health or worth as a potential surrogate.
What does the individual evaluation process actually involve for a BMI-over-30 candidate?
Where a clinic is willing to individually evaluate a candidate above its general BMI screening point, this typically includes additional baseline testing — blood pressure monitoring, a glucose tolerance assessment, and a more detailed review of any prior pregnancy complications — to build a fuller picture of metabolic and cardiovascular health beyond the BMI number alone. A candidate with a BMI over 30 but normal blood pressure, normal glucose tolerance, and a history of uncomplicated prior pregnancies presents a materially different risk profile than one with the same BMI and existing markers of metabolic strain, and clinics generally weigh this fuller picture in their determination.
Some candidates are advised that reaching a specific target BMI, even if still technically above 30, would materially improve their eligibility odds — this is why deferral with clear guidance, discussed generally in the requirements overview, applies here specifically: a candidate motivated to become a surrogate sometimes has a real, actionable path forward through a structured, medically supervised weight-management effort rather than a flat rejection.
Does BMI-related screening differ between the agency’s initial review and the clinic’s clinical determination?
An agency’s initial application review typically applies a general BMI guideline to decide whether to refer a candidate forward to clinical screening at all, while the actual eligibility determination is made by the receiving fertility clinic’s medical team based on the fuller evaluation described above — meaning a candidate who is initially screened out by one agency’s general guideline might still be a reasonable candidate under a different agency’s threshold or a specific clinic’s individualized review. This is why it is worth asking directly, rather than assuming, whether a specific agency’s stated BMI guideline is a hard initial cutoff or a starting point for individual clinical evaluation.
Is there a BMI level above which no individual evaluation is offered?
Yes — most clinics do apply some upper limit beyond which they will not proceed regardless of other health indicators, since risk increases with BMI and at some point outweighs what individualized evaluation can reasonably mitigate; this upper limit varies by clinic, which is another reason to ask a specific clinic directly rather than assuming a single industry-wide number applies.
Does BMI screening apply differently to egg donors versus gestational surrogates?
Yes — egg donor screening focuses on ovarian reserve and reproductive health markers relevant to egg retrieval, while gestational surrogate screening focuses on the physical capacity to safely carry a pregnancy to term, so BMI thresholds and their underlying rationale differ meaningfully between the two roles; this page addresses gestational surrogate screening specifically, not egg donor criteria.
Why does BMI specifically matter for a gestational surrogacy pregnancy, medically?
BMI is used as a screening proxy for pregnancy-related risks that increase with higher body weight, including gestational diabetes, preeclampsia, and complications during delivery — the concern is not cosmetic, it is about minimizing risk to both the surrogate and the pregnancy she is carrying for someone else.
Because the pregnancy involves an embryo that is not genetically the surrogate’s own, clinics and agencies generally apply a more conservative BMI threshold than they might for a woman’s own fertility treatment, reflecting the added duty of care toward the intended parents’ embryo.
Do all clinics apply the exact same BMI threshold?
No — thresholds vary somewhat by clinic and can depend on the specific embryo transfer protocol planned, so a candidate near the commonly cited BMI 32 cutoff should not assume automatic disqualification without a clinic-specific review.
What can a candidate do if her BMI is currently above the threshold?
Some candidates work with their own physician to bring BMI within range before reapplying, since the threshold reflects a specific clinical risk assessment rather than a fixed lifetime bar — a candidate whose BMI changes can reapply and be reevaluated.
How is BMI actually measured and confirmed during screening?
BMI is calculated from height and weight measured directly during the clinical screening visit rather than self-reported by the applicant, so an estimate given on the initial online application is treated as preliminary until confirmed in person.
Because BMI can fluctuate, some clinics allow a follow-up remeasurement if a candidate is close to the threshold and has made a documented change since the initial screening.
Does BMI interact with any other screening factor?
Yes — BMI is considered alongside other risk factors such as blood pressure and any history of gestational diabetes, since the clinical concern is the combined risk picture rather than BMI as an isolated number; a candidate with a borderline BMI but otherwise excellent health markers may be evaluated differently than one with multiple compounding risk factors.
What would disqualify someone permanently versus temporarily on this specific criterion?
BMI itself is not a permanent, fixed characteristic, so a candidate above the threshold today is not permanently excluded — if a candidate’s BMI changes and falls within range at a later point, she can reapply and be reevaluated on her current numbers, unlike some other disqualifying factors that do not change over time.
Is there a minimum BMI that also matters, not just a maximum?
Yes — clinics generally also set a minimum BMI threshold, since being significantly underweight carries its own pregnancy-related risks, so the review considers both ends of the range rather than only screening for a high BMI.
Are there any exceptions made for candidates with an otherwise exceptionally strong medical profile?
The BMI threshold reflects a specific, evidence-based clinical risk assessment rather than an arbitrary cutoff, so exceptions are uncommon and made only at the discretion of the reviewing physician based on the complete clinical picture — a candidate should not assume an exception will be made and should instead treat the published threshold as the standard to plan around.
That said, borderline cases are exactly why the in-person clinical measurement and full health review exist — a candidate close to the threshold with strong overall health markers is evaluated on the complete picture, not automatically excluded based on a preliminary self-reported estimate.
How does BMI screening compare across the surrogacy industry generally?
BMI thresholds in this general range are standard across most reputable gestational surrogacy programs and reflect broadly shared clinical guidance in the field, rather than being a policy unique to any single agency — a candidate screened out for BMI at one clinic is likely to encounter a similar threshold elsewhere, though exact cutoffs can vary somewhat by clinic.
Does this page recommend a specific diet or weight-loss program for a candidate near the threshold?
No — this page does not recommend a specific program, since any weight-management approach should be guided by the candidate’s own physician based on her individual health, not a generic recommendation from an educational resource.
What is the final, practical takeaway for a candidate close to this threshold?
Apply and let the clinical measurement and full health review make the determination, rather than self-disqualifying based on an estimate — many borderline candidates are approved once the complete picture is reviewed.
Does BMI screening ever get revisited if a candidate is in the middle of the matching process?
Yes — because matching, contracting, and medical clearance can take months, a candidate’s weight is generally reconfirmed close to the actual transfer date, not just at initial application, to make sure the clinical picture used for the transfer decision is current.
This is standard practice across the industry rather than something unique to any one program, and it protects the candidate as much as it protects the timeline, since a transfer is only scheduled once the treating physician confirms current health markers support it.
Is there a difference between BMI screening for a first-time surrogate and a repeat surrogate returning after her own pregnancy?
The threshold itself does not change based on surrogacy history, but a repeat surrogate’s weight can shift after her own delivery and recovery, so she is measured fresh for the new cycle rather than being cleared automatically based on a prior journey’s numbers.
Frequently Asked Questions
What is the main point of surrogate BMI requirements?
BMI thresholds vary by clinic and a BMI over 30 is often grounds for individualized review — considering blood pressure and glucose tolerance — rather than an automatic disqualification everywhere.
Who makes the final medical decision?
The receiving fertility clinic’s reproductive endocrinologist makes the clinical eligibility determination.
Does a published number guarantee my result?
No. Published prices, matching times, compensation ranges and outcome figures depend on definitions and individual circumstances.
Why does independent escrow matter here?
It doesn’t directly relate to BMI screening — escrow is a separate financial safeguard applied once matching and compensation begin.
How should missing public information be interpreted?
Missing information means the research did not verify a comparable public disclosure, not evidence of an unfavorable practice.
Does FDA registration mean FDA approval?
No. Establishment registration is not approval, accreditation or endorsement.
What BMI range do most clinics use as a starting point?
Thresholds commonly cluster in the low-to-mid 30s, but this varies by clinic — confirm the specific current policy directly.
Can losing weight change eligibility?
For some candidates, yes — ask the specific clinic whether a lower BMI at a future date would change the evaluation.
What should I put in writing?
Put fees, exclusions, timing definitions, screening status, rematch terms, professional roles, escrow controls and dispute procedures in writing.
Where can documented corrections be sent?
Send source-backed corrections to rankings@surrogacy4all.com.
About the Authors
Shweta Rathod, MD – Doctor of Medicine; clinical experience in Obstetrics and Gynecology, labour room management, and IVF. Medically reviewed by Rashmi Gulati, MD – Board Certified, Internal Medicine; Medical Advisor, Surrogacy4All; privileges at Mount Sinai Hospital. Meet the team.
Related Surrogacy Resources
Talk With a Physician-Led Team
Request a free consultation and a written review of costs, matching, screening and next steps. Call (212) 661-7673 or email info@surrogacy4all.com.
Methodology and Disclosure
This page is produced by DGA, Inc. (Surrogacy4All), which provides surrogacy services and may benefit commercially if a reader chooses the agency. No agency pays for placement in the Surrogacy4All rankings. Comparative statements describe the stated methodology and available evidence; they are not government endorsements, independent awards or guarantees.
Send documented corrections to rankings@surrogacy4all.com.

Dr. Shweta Rathod
- Dr. Shweta Rathod

- Dr. Shweta Rathod
- Dr. Shweta Rathod
- Dr. Shweta Rathod